Healthcare generates more data than almost any other sector — and yet most of it sits unused. Administrative staff and technology costs account for 25–35% of all U.S. healthcare spending — a burden that spans staffing, technology, and the operational overhead of a heavily regulated system. For healthcare organizations trying to change that, the constraint isn't AI capability — it's data infrastructure. The systems making the most progress are those that figured out how to make their data accessible to AI before they tried to apply it.
Healthcare produces an extraordinary volume of data. Healthcare's data volume is staggering — and growing. A large hospital system now generates terabytes of data daily, spread across clinical notes, lab results, billing records, and imaging archives. The challenge is that this data is not in one place and is not in one format.
The challenge is that roughly 75% of that data is unstructured. Clinical notes and other free-text clinical documents are written in natural language rather than structured fields. Standard analytics tools cannot query them directly. AI can — but only once that data has been extracted and made accessible.
For health systems still running fragmented EHR environments, that prerequisite is itself a significant undertaking.
Most public discussion of AI in healthcare focuses on diagnostics — and the case is compelling. Machine learning models applied to radiology data can flag anomalies in imaging that a human reviewer might miss. With approximately 95 million MRI scans performed globally each year, even incremental improvement in read accuracy translates to meaningful clinical impact.
But AI in healthcare extends well beyond the clinical use case. Administrative automation is where organizations are finding the most immediate, measurable return. Prior authorization, claims processing, coding and scheduling work — these are high-volume, rule-bound processes where AI performs reliably and reduces the per-transaction cost substantially. The administrative burden in healthcare is a problem that pre-dates AI, but it is also where AI can deliver the fastest measurable returns.
The longer-horizon vision is a healthcare system that is genuinely proactive rather than reactive — one that uses a patient's full data history to anticipate care needs and reduce avoidable interventions.
For that future to work, interoperability is not optional. AI models trained on data from one EHR system cannot be reliably applied to data from another unless the two share a common schema or the data has been normalized. Health systems often run dozens of distinct systems — EHR platforms, billing tools, lab applications, specialty systems — that do not share a common data model. The question isn't whether healthcare needs to change — it does. The more useful question is where AI can begin to address the structural challenges that have resisted change for decades.
The organizations making the most progress are those that have invested early in the data infrastructure layer: extracting and standardizing data before attempting to apply AI on top of it. The payoff is not just AI readiness. Interoperability itself reduces administrative errors and helps the organization adapt as care models evolve.
The administrative case is strong on its own terms. Administrative staff and technology costs account for 25–35% of all U.S. healthcare spending. That is a large surface area for AI to work on — and a relatively low-risk starting point compared to clinical applications, where the stakes for model error are higher.
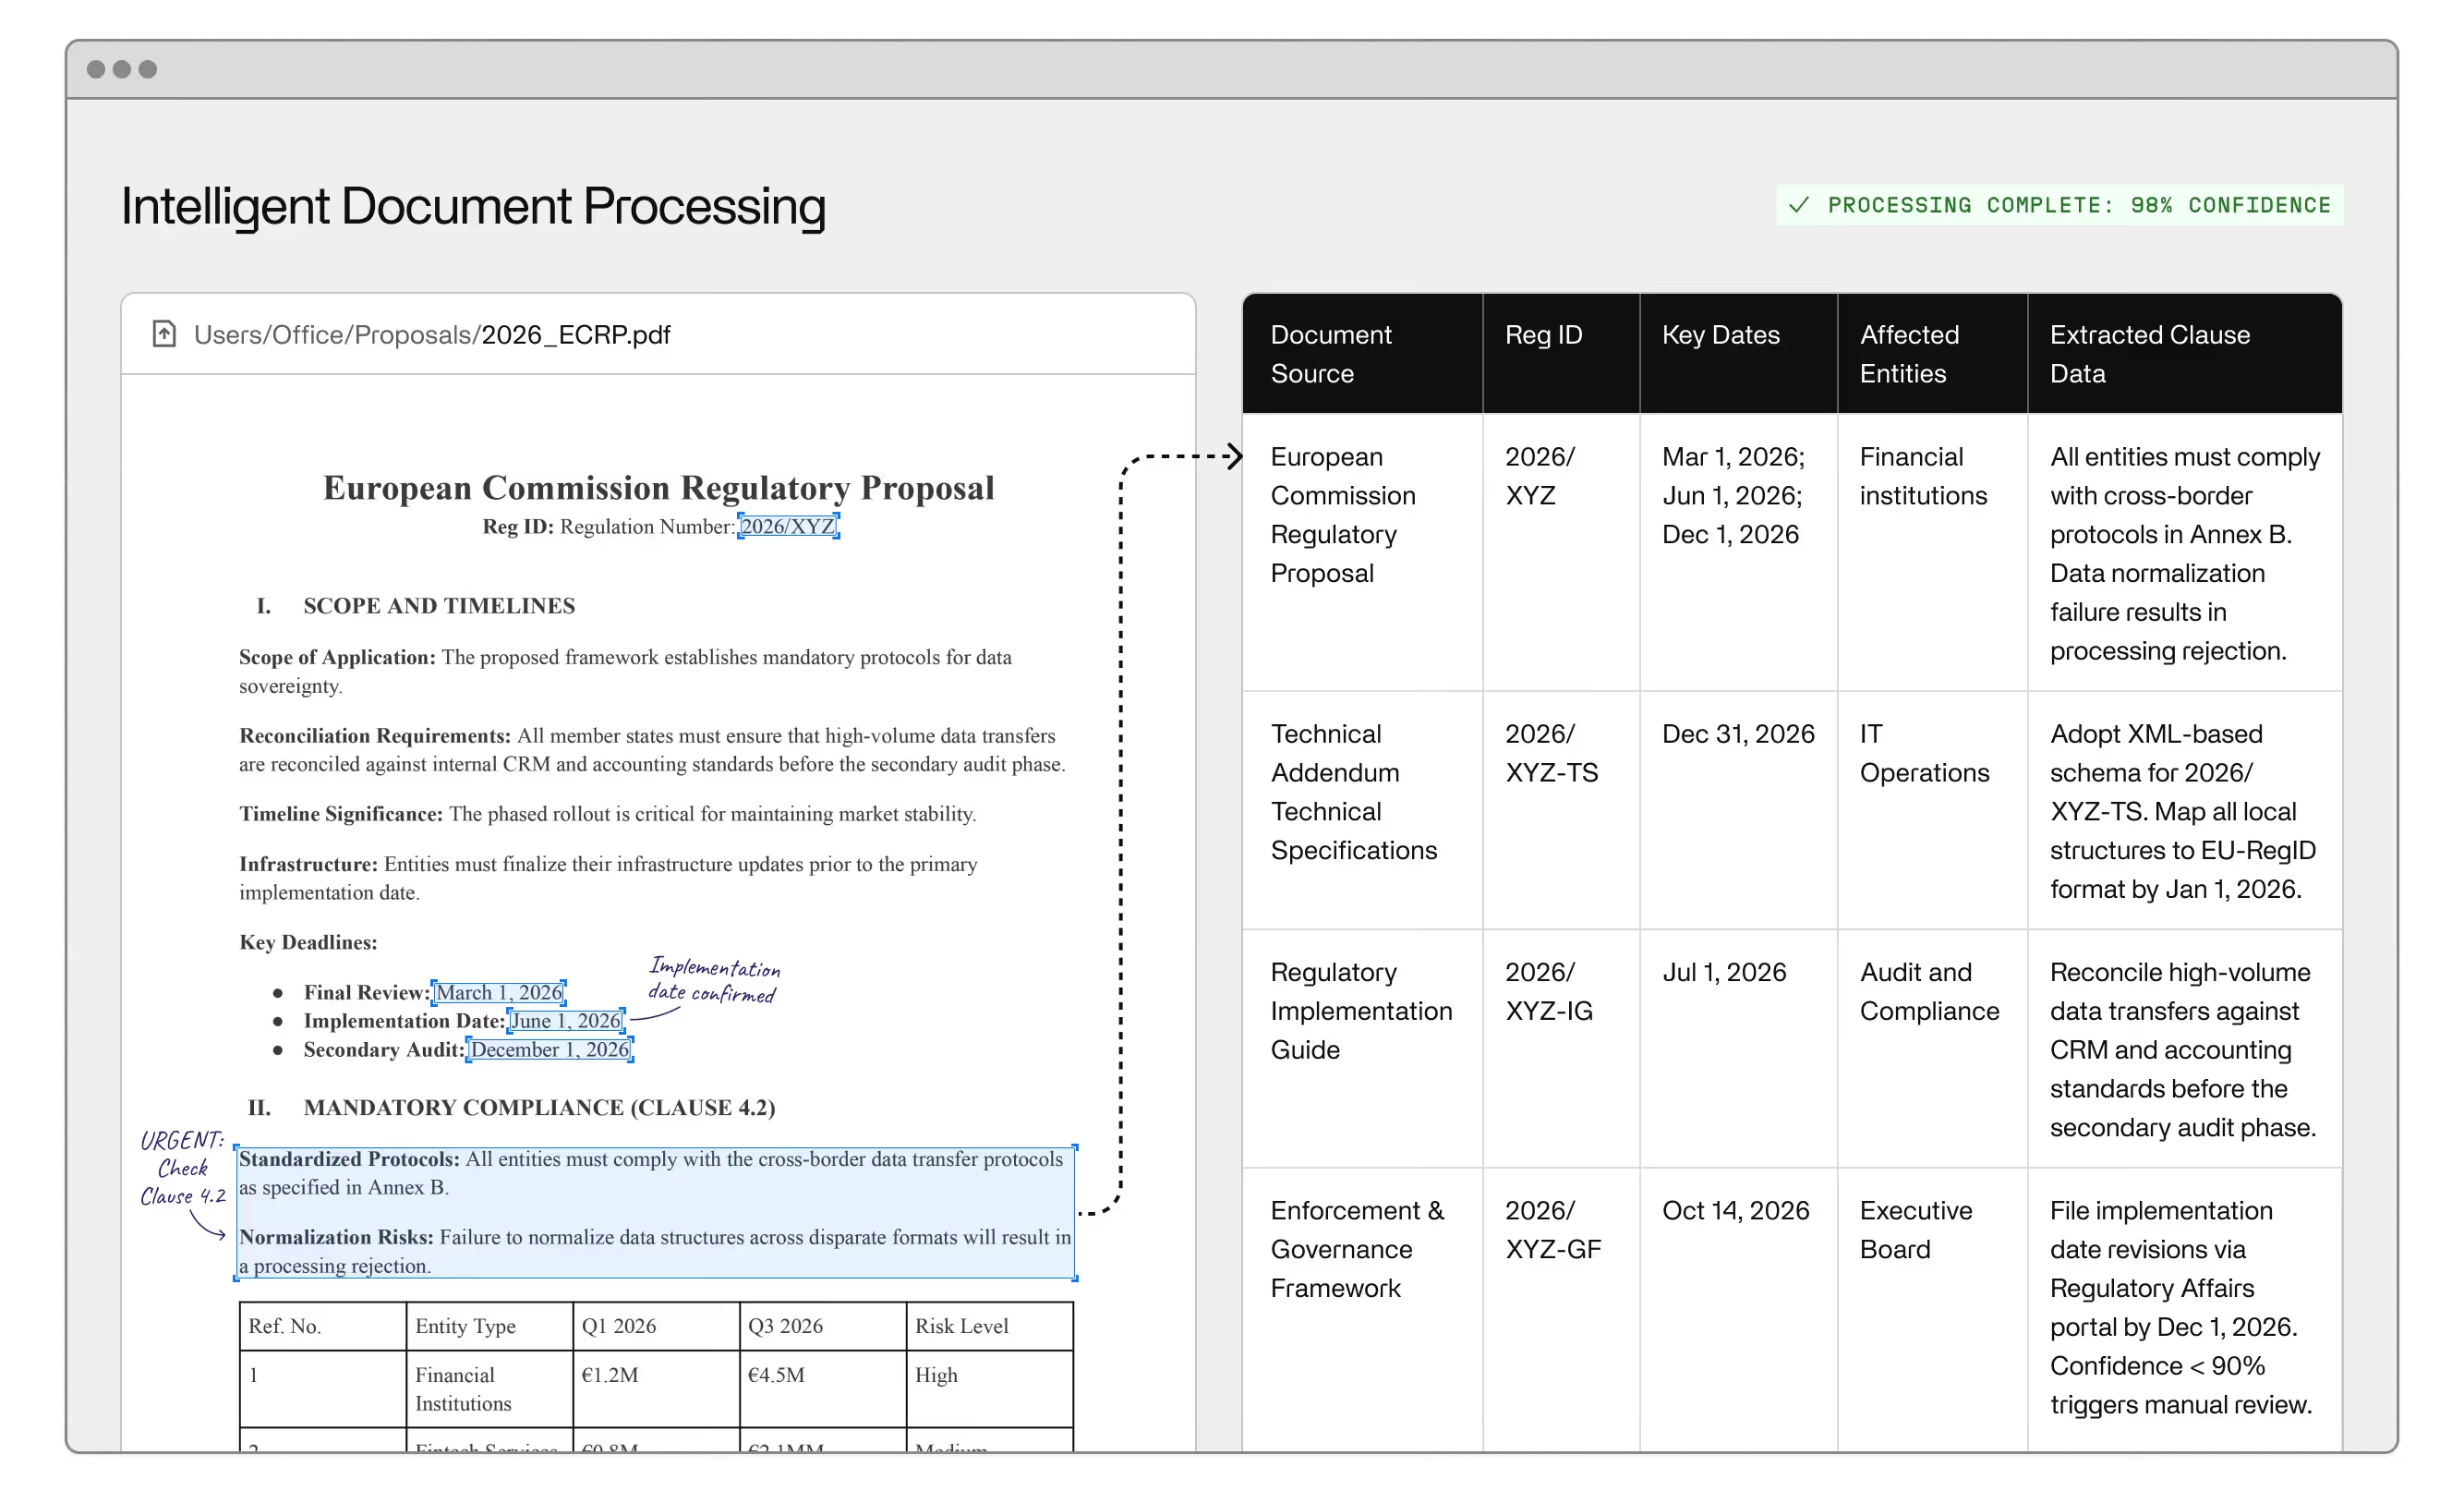
Where do organizations begin? Typically, the first step is an audit of what data they actually have and in what form — what is in structured fields, what is in free text, and what systems are not talking to each other. That audit almost always surfaces opportunities for immediate automation: forms that could be pre-populated, records that could be auto-coded, workflows that could be routed based on content rather than manually triaged. Organizations that have mapped this path in detail — from initial assessment to deployed AI — have found that a structured implementation approach materially reduces the typical runway.
Invisible partners with healthcare organizations on data infrastructure, process automation, and AI readiness. Get in touch to learn how we work with healthcare teams.
Big data gives AI systems the volume and variety of inputs needed to learn meaningful patterns. In healthcare, that means training models across the full range of clinical and operational records simultaneously. Without structured access to that data, AI can process inputs in isolation but cannot generalize usefully across a patient population or operational context.
Most clinical documentation — physician notes, discharge summaries, imaging reports — is captured as free text rather than structured fields. Add in audio recordings and scanned documents, and roughly 75% of health data ends up in formats that standard analytics tools cannot query directly. That proportion has grown as the volume of data per patient has increased.
The most established AI applications are in administrative automation — the high-volume work of prior authorization and claims processing where AI reduces per-transaction cost without requiring clinical judgment. AI is also being applied to clinical documentation — reducing the note-taking burden on physicians — and to supply chain and demand forecasting for health systems managing staffing and inventory across multiple facilities.
Data interoperability remains the central constraint. Health systems often run dozens of distinct systems — EHR platforms, billing tools, lab applications, specialty systems — that do not share a common schema. Beyond that, regulatory requirements — HIPAA compliance and clinical validation standards for AI-assisted decisions — mean that implementation timelines in healthcare are longer than in most other sectors.
Interoperability means different systems can share data in a consistent format, so an AI model trained on one dataset can be validated against another. For health systems, this matters most at the point of care: a clinician making a decision should be able to draw on imaging data and medication history from multiple sources — not just the records that happen to be in one system.